


Oral Surgery Temecula Patients Trust: One Doctor, One Plan, No Handoffs
October 5, 2026
October 5, 2026
At some point after fifty, most people hear some version of the same sentence: this one can't be saved.
What follows is usually brisk. The dentist explains that the extraction is beyond what the office handles, writes down a name, and tells you someone will call to schedule. You leave with a referral and the sense that the hard part has been settled.
It hasn't.
The question almost every patient asks at that appointment is whether to go through with the surgery. It's the wrong question, or at least the less consequential one. Oral surgery is rarely the end of anything. An extraction is the beginning of whatever gets built in its place, and bone grafting exists specifically to make that next step possible. The real question is who holds the plan around the procedure, because the plan is what determines whether the work still holds in five years.
Here is the part nobody explains at the referral. Most oral surgery in the Temecula Valley is performed by a provider who will never see the finished result. They handle the procedure competently, address the tooth in front of them, and send you back to a dental office across town to build on top of it. Each person does their part. No one is responsible for the whole.
For adults managing missing teeth, failing restorations, and the oral health decisions that carry the most weight of their lives, that gap is where outcomes quietly go wrong. And it's avoidable.

The gap rarely announces itself.
Picture a sixty-three-year-old contractor in Murrieta whose lower molar finally gave out under a crown he'd already had replaced once. His dentist takes an X-ray, confirms the tooth can't be saved, and hands him a name. Two weeks later he's writing out his medical history for the second time in a month, in a waiting room he's never sat in.
He meets the oral surgeon about four minutes before the procedure.
The surgeon is good at his job. What he doesn't have is the treatment plan. He doesn't know about the bridge on the opposite side, the partial denture that's lived in a drawer for three years, or the conversation about dental implants from back in March. That absence is routine. In one review of patient files at an oral medicine service, only 30 percent arrived with a referral letter at all, and 84 percent of those letters omitted a clinical diagnosis. (Navarro et al., International Journal of Oral and Maxillofacial Surgery)
The extraction goes well. Twenty minutes, a few sutures, printed instructions.
What wasn't decided that morning is whether the socket should have been grafted at the same time. That call belongs to whoever is planning the implant, and nobody in the room that day was planning the implant.
So the site heals on its own. A systematic review of human re-entry studies found horizontal bone loss of 29 to 63 percent within six months of extraction, with the sharpest reductions in the first three months.
He returns to his dentist for the implant consultation he'd been counting on all along.
The scan settles it. The ridge doesn't have enough width left to place the implant. That means having to go back and get bone grafting, the same procedure that could have happened during the original surgery. It means a second surgical appointment, with its own recovery time. And it means another four to six months before an implant can even be placed, on top of the eight months already gone.
The cost isn't just time. It's a second surgery he wouldn't have needed if the extraction and the implant had been planned together, and months of healing added onto months he's already spent waiting.
Nobody did anything wrong. The oral surgeon completed the procedure he was asked to complete. The dentist referred out work his office doesn't handle. Two competent providers, one outcome that fell short, and no one who can say where it went sideways.
That's the cost of dental surgery performed outside the plan it belongs to.
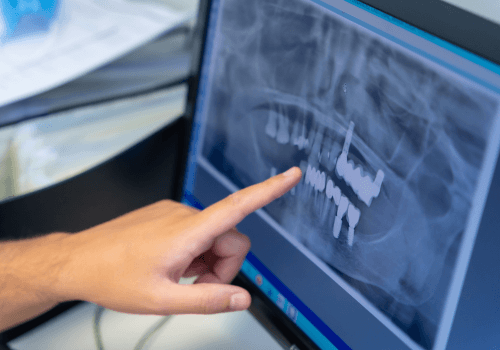
To understand why that plan matters so much, it helps to be clear about what oral surgery is and what it isn't.
It isn't a category of last resort. Oral surgery covers the procedures that form the foundation of complex dental treatment, from wisdom tooth removal and bone grafting to corrective jaw surgery and implant preparation. It's the work that has to happen before a reconstruction, a bridge, or a set of dental implants can be built at all. Three procedures do most of the heavy lifting.
Extractions are the starting point. Wisdom tooth extractions, a tooth fractured below the gumline, a root that has failed under an old crown, decay that has run past what a restoration can hold. Removing it stops the damage, and oral surgeons perform over 42,000 tooth extractions annually, including common wisdom teeth removal cases, which is often necessary for many people who may choose sedation options for comfort during those treatments. It also raises a question that has to be answered the same day: what goes in its place, and when.
The jawbone around a tooth exists because the tooth is there. Once it's gone, the ridge begins to shrink, and that bone loss is what eventually makes a site unusable. Bone grafting rebuilds that structure. Done at the right moment, it preserves options. Done late, it becomes a separate surgery with its own healing timeline.
Surgical preparation is the least visible of the three and the most decisive. It creates the conditions an implant needs to integrate and stay integrated, and dental implants replace missing teeth with titanium posts that fuse with bone, which is the difference between a restoration that lasts twenty years and one that comes loose in four. Surgical preparation may also support full mouth dental implants when multiple teeth or full arches are being restored.
Read those three together, and the pattern is obvious. None of them is a standalone event. Each one is foundation work, and foundation work is defined entirely by what gets built on top of it. The decision about how to replace missing teeth determines how the surgery should be performed in the first place. Severe bone loss can require different techniques, including zygomatic implants anchored in the cheekbone.

Separation is the default in dentistry, and it's worth asking why.
The usual explanation is capability. Surgical work requires training and equipment many general practices don't have, so it goes out the door. For a narrow set of complex cases, that's the right call. It has also quietly become the standard answer for routine extractions and implant preparation, and the reason there is closer to economics than to clinical judgment.
The cost lands on the patient in a way nobody itemizes.
Every surgical procedure involves two decisions. There's the procedure itself, which any competent maxillofacial surgeon or oral surgeon can perform. Then there's how it should be done given everything else happening in the mouth: whether to graft, how much jawbone to preserve, what timeline leaves the site ready when the rest of the treatment plan arrives.
The second decision requires knowing the whole case. It's also the one that determines outcomes five years out.
You could see three or four different providers to get through a complex case. One dentist to diagnose, another oral surgeon to extract, a third to graft, a fourth to place the implant. Each one meets you for the first time, works off a single X-ray, and moves on once their part is done.
Or you can choose one doctor who does all of it.
That's the better choice, and here's why. The doctor who plans your treatment should be the doctor who does your surgery. When one doctor handles both, bone loss gets caught early instead of found later. The implant gets planned before the tooth even comes out.
One doctor also means fewer appointments, less time spent retelling your history, and lower costs, since nothing gets repeated or lost in a referral letter. And when a decision needs to be made, one person can make it, because one person knows your whole story and what you need. That's what exceptional care looks like: not a string of appointments with strangers, but one doctor who sees the whole case through.
Only a few practices still work this way on purpose. For patients with complex cases, finding one of them is the first step that changes everything after it.

Those practices exist in the Temecula Valley. One of them has been here since 1982.
The Center for Adult Dentistry is structured around a single patient population: adults 50 and older facing the most consequential oral health decisions of their lives. That focus isn't marketing language. It shapes the clinical model because aging dentition, decades of prior dental work, and the financial weight of major reconstruction are not problems a general-population practice is built to solve.
Patients arrive from Temecula, Murrieta, Menifee, Fallbrook, and the California wine country communities in between. Most have been referred out before.
Dr. Dave Cutts has practiced dentistry in this valley since 1982. He built his clinical foundation broadly, including oral surgery and extractions, before narrowing deliberately into advanced training in adult complex dentistry and full mouth reconstruction.
That sequence matters. The range required to handle complex cases in-house isn't something a practice adopts later; it comes from forty-plus years of doing the work other offices send away, and strong reviews often pair those skills with praise for staff kindness and effective pain management during surgery. One longtime patient came in after another practice told him the tooth needed a specialist with specialty equipment. Dr. Cutts performed the procedure himself. The patient still has the tooth.
Extractions, bone grafting, and surgical preparation for dental implants are all performed at the office by Dr. Cutts.
No referral out. No unfamiliar surgeon. No repeating a history that already exists in the chart across the hall. Because he holds the complete treatment plan, he makes the surgical decisions described in the last section, whether to graft, how much ridge to preserve, when to place, with the whole case in view rather than one tooth at a time.
The rarer advantage is what happens after surgery.
Most practices outsource prosthetic fabrication, which introduces weeks of delay, variable quality control, and a communication gap between the person treating the patient and the person building the restoration. The Center for Adult Dentistry has a master laboratory technician on site. Dentures, implant restorations, and full-arch work are fabricated in the building, adjusted with immediate feedback, and fitted without shipping anything anywhere.
For patients who have already paid for restorations that never fit right, this is usually the first time something is corrected in an afternoon instead of a month.
An afternoon instead of a month is the pattern, and it starts long before anything gets fabricated.
The first step is an appointment that costs nothing and commits you to nothing.
Dr. Cutts performs a full oral examination himself and takes up to three diagnostic X-rays at no charge. Then you sit down for an unhurried one-on-one conversation where he explains what he found in plain language and answers every question you brought. If you're carrying anxiety about what's coming, this is where it gets addressed, before anyone talks about scheduling.
You leave with a complete, itemized treatment plan listing every option and its associated pricing. That's the whole visit. There's no pressure to schedule, and plenty of people don't on the day.
Once you decide to move forward, the surgical work gets sequenced inside the full picture rather than booked as its own event.
The order of procedures, the technique used, whether bone grafting happens at the same appointment as the extraction, and how long the site needs before dental implants can be placed are all determined with what comes before and after already accounted for. Diagnostic imaging technology makes the planning specific rather than approximate, because you can see the jaws and the available bone before deciding anything.
This is the step that doesn't exist when surgery is referred out. The surgeon on the other end has no larger plan to fit the procedure into.
Extractions, bone grafting, and implant preparation are performed at the office by the same doctor who built the plan.
You're not meeting anyone new. Your history's already in the room, which matters more than most patients realize. Anesthesia is the part of dental medicine where knowing the whole patient counts most, and administering it safely takes extensive training plus a current picture of medications, conditions, and prior reactions. Most surgical procedures here are completed under local anesthesia. For patients who've been avoiding the chair for years, sedation dentistry makes the appointment possible.
The benefits of doing it this way are practical rather than abstract. Fewer appointments. No history repeated. No gap between the person who planned the surgery and the person holding the instruments.
Recovery gets monitored as a standing part of your care, not something you're left to assess alone.
You'll know what to expect before you leave: what's normal at day two, what swelling should look like by day four, and which signs of infection warrant a call. Most people are through the worst of it inside a week.
If something doesn't look right, you call us. Complications are handled by the doctor who performed the surgery, without a referral, a new consultation, or a week of waiting to be seen. We reserve appointment slots specifically for urgent needs, so you're not left waiting weeks to be seen.
Treatment ends. The relationship doesn't.
The same doctor and the same team stay your dental home, which means the person evaluating your implant in year six is the person who placed it. That continuity is what lets you maintain the work rather than rediscover problems late, and it's where a forty-year commitment to one community shows up in something measurable.
Compared with starting over somewhere new every time a problem surfaces, there's no contest.
The contractor in Murrieta didn't get a bad surgeon. He got a good one who'd never seen his case.
That's the distinction worth holding onto. When someone hands you a referral slip and a name, the question isn't whether that person is qualified. It's whether they'll be working from your complete treatment plan or from a single X-ray taken that morning, and if you're seeing an outside oral surgeon, a practical screening question is whether they're board certified by the American Board of Oral and Maxillofacial Surgery.
If you're weighing oral surgery in Temecula right now, there's a cheap way to find out where you stand. Schedule a free consultation with Dr. Cutts, and you'll get a full oral examination, up to three diagnostic X-rays, an unhurried conversation about what he found, and a complete itemized treatment plan with every option and its price. We strive to keep planning, surgery, and follow-up under one roof. It's a $500 value, and it costs you nothing.
You're also not obligated to schedule anything after it. Some patients come in for a straight second opinion on a plan they've already been given somewhere else, decide it was reasonable, and go back. That's a fine outcome. The point is leaving with an honest picture of your oral health instead of a decision you made because someone was waiting on you.
An oral surgery specialist handles the surgical procedures outside routine dental care: removing teeth that can't be saved, rebuilding bone lost to missing teeth, and preparing the jaw to hold an implant.
Most people searching for a Temecula oral surgery specialist want someone capable of handling the surgical part of their case, not a particular title. The better question is whether that person is working from your complete treatment plan or meeting you the morning of the procedure. At The Center for Adult Dentistry, extractions, bone grafting, and implant preparation are performed in-house by Dr. Cutts, who's spent four decades on the complex cases most practices refer out.
You can. What you give up is sequencing.
A surgeon seeing your case cold decides in isolation, which is how a site ends up needing bone grafting eight months after an extraction that could've been grafted the same day. The alternative is one consultation that produces one treatment plan with the surgical work built into it. That's the first step worth taking, and it isn't a referral to anywhere else.
It depends on what the case requires, and anyone quoting a number before examining you is guessing.
The free consultation produces a fully itemized treatment plan with every option and its price, so you see what the procedure costs before anything is scheduled. Flexible financing is available for comprehensive cases.
Coverage varies by plan and by procedure. Surgical extractions are often treated differently than the restorative work built on top of them, which can catch patients off guard.
The consultation is where that gets sorted. You'll have the itemized plan in hand and can work through costs and coverage before committing. Worth saying plainly: if your budget begins and ends with what insurance covers, another practice may be the better fit.
No.
The doctor who evaluates your case is the doctor who performs your surgery and monitors your recovery. Extractions, bone grafting, and implant preparation are handled in-house by Dr. Cutts, which helps preserve comfort, continuity, and your smile because the same office manages follow-up if anything changes. If something isn't right six months from now, you call the same office and see the same doctor, with ongoing monitoring that can also catch oral-health changes linked to other diseases.
You’ve dealt with the pain, discomfort, and anxiety long enough.
Sign up for a free consultation with Dr. Cutts and get a treatment plan built around your actual needs.


The Center for Adult Dentistry is a Temecula dental practice built for adults 55 and older. We restore function, confidence, and the freedom to fully enjoy the life you have worked so hard to build.

43057 Margarita Rd #101 Temecula, CA 92592

877-628-1735
79440 Corporate Centre Dr, #103 La Quinta, CA 92247

8:00AM - 5:00PM
8:00AM - 2:00PM

By Appointment Only
Closed